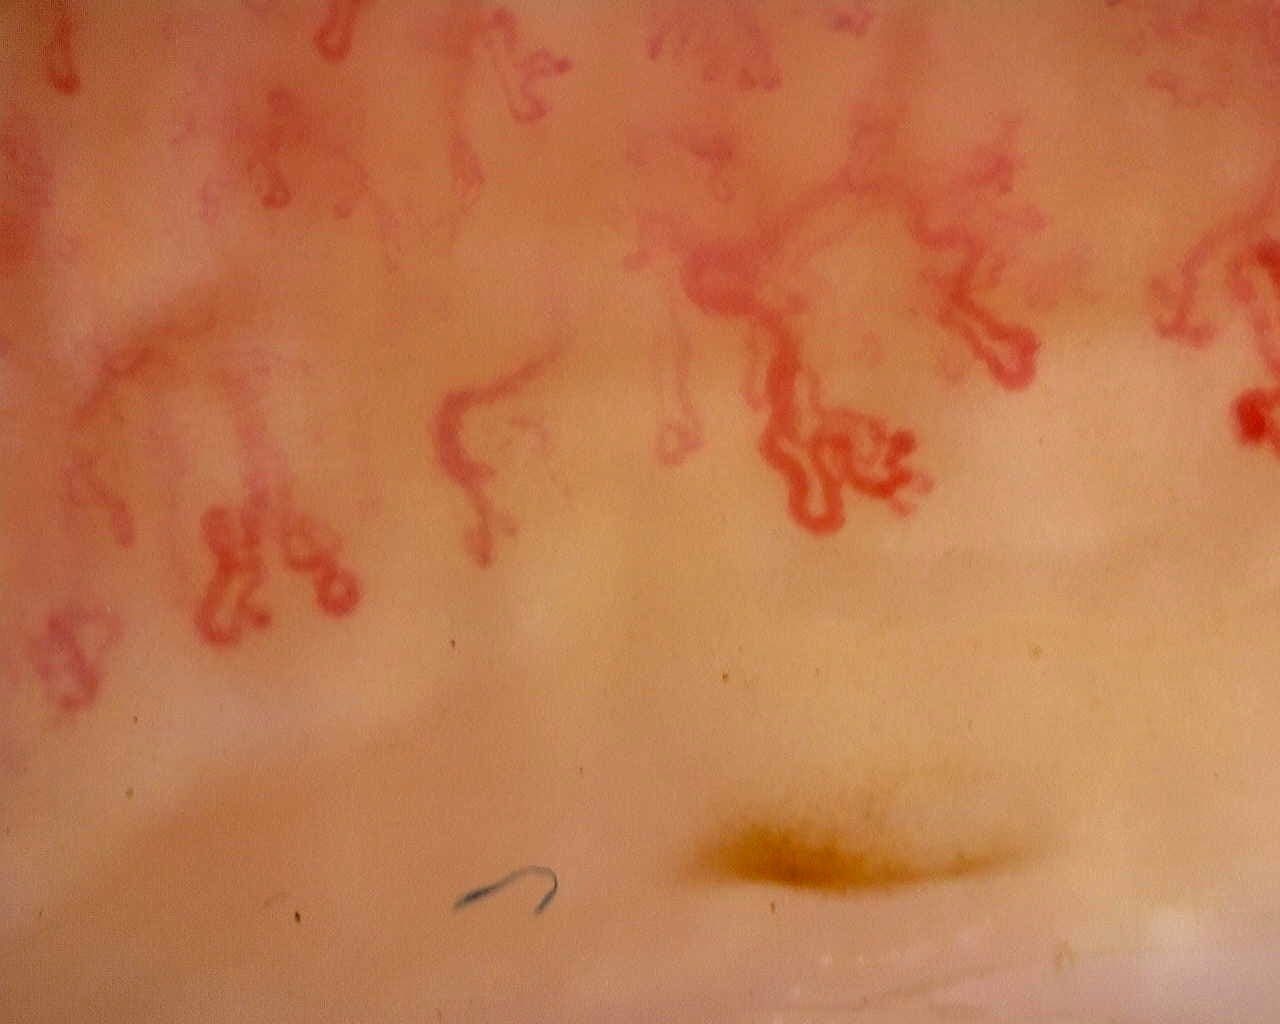
Irregular, ramified loops in a field from the late-pattern reference study. The full study provides context for capillary loss and distribution.
- Magnification:
- 212.3×
- Device:
- Dino-Lite Edge
- Field of view (W × H):
- ≈ 1.84 × 1.47 mm
How to assess and measure
Quantify density in assessable distal-row segments and describe the extent of avascular areas, disorganization and abnormal shapes. Compare multiple fingers and distinguish true loss from poor visibility. A late pattern is an overall classification; some fields can retain giants or show relatively preserved architecture.
Interpretation and related diseases
Fewer giant capillaries do not necessarily mean less microvascular damage. The anti-U3 RNP case illustrates disagreement between an automated active classification and the final late-pattern interpretation. The inter-digit heterogeneity case shows why representative fields and the final report need to be read together.
Read the detailed clinical chapterCommon mistakes
- Interpreting absence of many giants as a normal study.
- Letting one preserved finger overrule marked damage elsewhere.
- Treating a late pattern as proof of disease duration, inevitable progression or a specific organ complication.
Real images and comparisons
Captions distinguish the illustrated finding from the study interpretation. Comparisons include variants, other clinical contexts or artifacts where available.
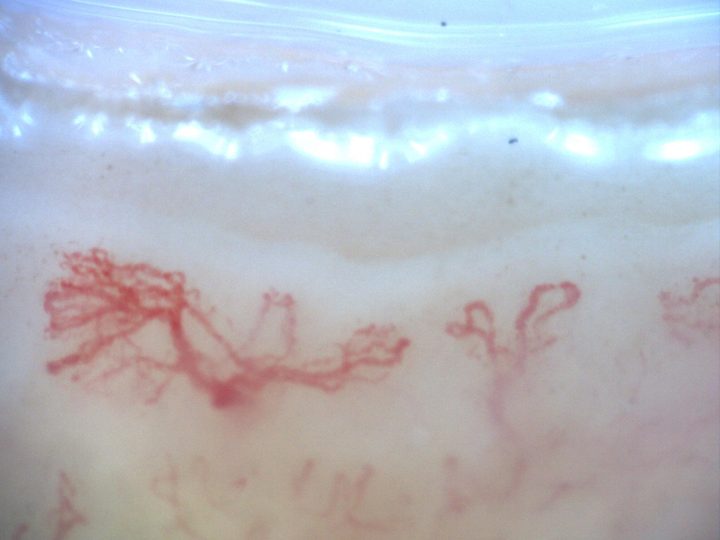
200x capillaroscopy image from a patient with systemic sclerosis showing a late pattern with marked disorganization and neoangiogenesis, without visible megacapillaries.
- Magnification:
- 200×
- Device:
- Inspectis Digital Capillaroscope
- Field of view (W × H):
- ≈ 1.68 × 1.26 mm
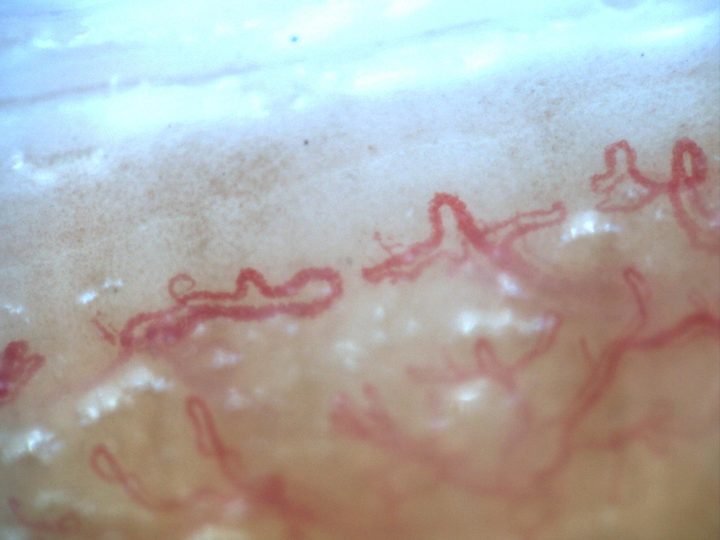
Second 200x capillaroscopy image from systemic sclerosis with a late pattern, marked disorganization, and neoangiogenesis.
- Magnification:
- 200×
- Device:
- Inspectis Digital Capillaroscope
- Field of view (W × H):
- ≈ 1.68 × 1.26 mm
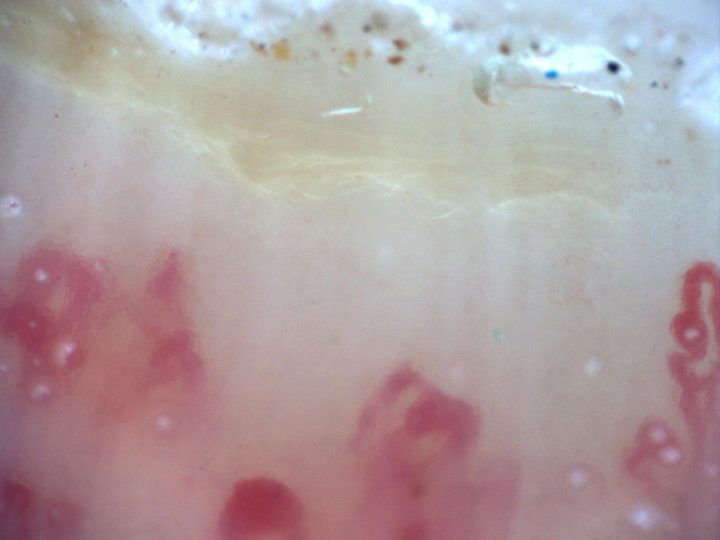
200x capillaroscopy image showing an extensive capillary-free space compatible with an avascular area.
- Magnification:
- 200×
- Device:
- Inspectis Digital Capillaroscope
- Field of view (W × H):
- ≈ 1.68 × 1.26 mm
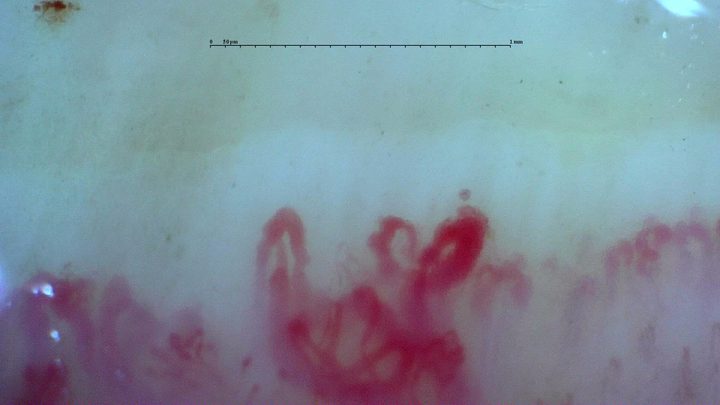
Irregular enlarged loops in the anti-U3 RNP case. Although giants remain present, the final report classifies the overall microangiopathy as late.
- Magnification:
- 250×
- Device:
- Smart G-Scope
- Field of view (W × H):
- ≈ 2.39 × 1.34 mm
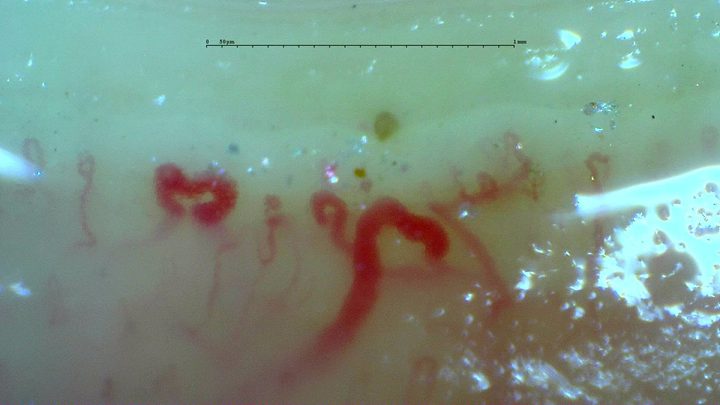
A disorganized field with enlarged loops and surface reflections from the inter-digit heterogeneity case. Other fields differ markedly; inspect the full study and its image-quality caveats.
- Magnification:
- 250×
- Device:
- Smart G-Scope
- Field of view (W × H):
- ≈ 2.32 × 1.31 mm
Complete cases and studies
Late SSc Cutolo Pattern: Representative Case
The study shows severe capillary rarefaction, avascular areas, disorganization, and ramified or highly abnormal capillaries.
Systemic Sclerosis with anti-U3 RNP: Late Microangiopathy
There is marked capillary loss (4.9/mm), architectural disorganization, frequent dilations, giant capillaries in 14.9% of capillaries, and abnormal or ramified forms. This pattern was classified by the CAPI-Detect algorithm as active; however, due to the frequent features characteristic of late-stage involvement, it was ultimately classified as such in the final report.
Anticentromere-Positive Systemic Sclerosis with Inter-Digit Pattern Heterogeneity
The study is notable for pronounced inter-digit and inter-field heterogeneity. L4C shows marked capillary loss (desertification), whereas L4A has relatively preserved, normal-appearing architecture. R2C and L3D show giant capillaries within a disorganized architecture. R4A demonstrates late-stage revascularization or neoangiogenesis—a morphology the contributor describes as a "post-late" pattern—while R5A shows transitional active-to-late features. The complete study is classified as a late scleroderma pattern, with a mean capillary density of 5.63/mm, enlarged capillaries in 43.5%, and giant capillaries in 2.5%. Image quality is variable; several fields are technically limited and should not be interpreted in isolation.
References
- Smith V, et al. Standardisation of nailfold capillaroscopy for the assessment of patients with Raynaud’s phenomenon and systemic sclerosis. Autoimmun Rev. 2020;19:102458.
- Cutolo M, et al. Nailfold videocapillaroscopy assessment of microvascular damage in systemic sclerosis. J Rheumatol. 2000;27:155–160.
- Ingegnoli F, et al. Reporting items for capillaroscopy in clinical research on musculoskeletal diseases: a systematic review and international Delphi consensus. Rheumatology. 2021;60:1410–1418.
Scientific advisory board and contributors · Editorial policy